
 See Our Latest Article on HelloNation
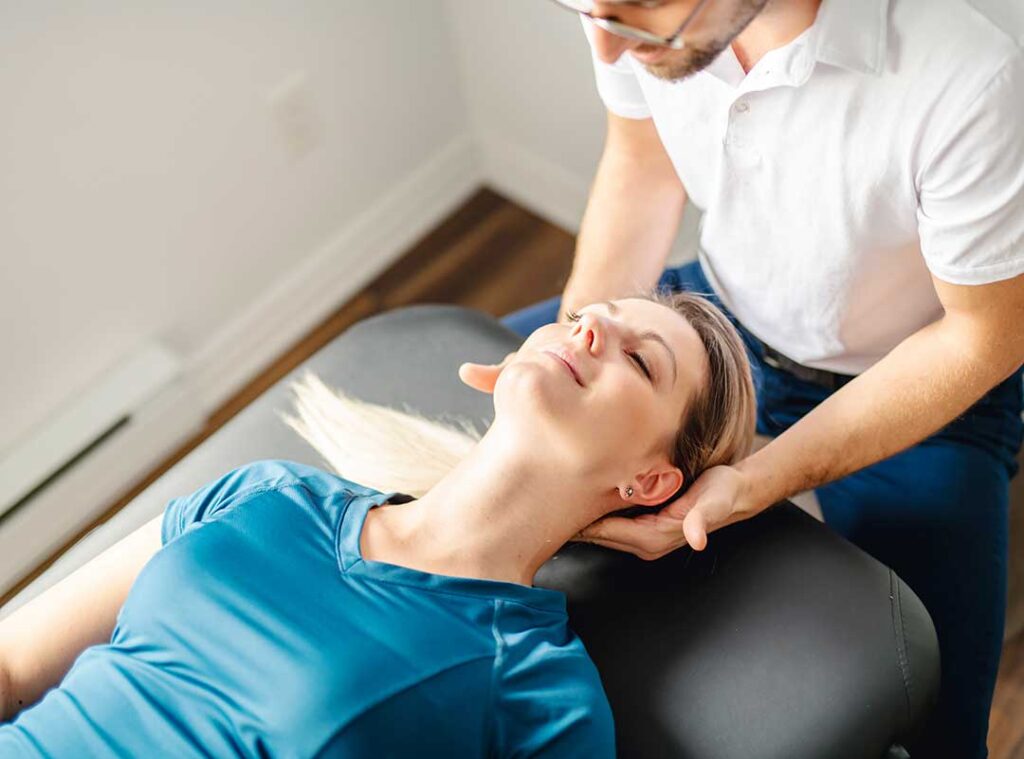
Vertigo is a sensation that you or the room is spinning, tilting, or moving when it is not. Chiropractic care may help some people whose dizziness is connected to neck pain, restricted neck movement, or muscle and joint problems, but it is not a universal treatment for vertigo and should not replace medical evaluation.
What causes vertigo?
Vertigo is a symptom rather than a single diagnosis. The most common causes involve the inner ear, which helps the brain understand head movement and balance.
Benign paroxysmal positional vertigo, or BPPV, is one frequent cause. It occurs when tiny calcium particles inside the inner ear move into a location where they send confusing motion signals to the brain. Symptoms often begin when rolling over in bed, looking upward, bending down, or sitting up. Episodes may be brief but intense, sometimes accompanied by nausea or unsteadiness. ([my.clevelandclinic.org](https://my.clevelandclinic.org/health/diseases/11858-benign-paroxysmal-positional-vertigo-bppv?utm_source=openai))
Other possible causes include:
- Inner-ear inflammation or infection
- Vestibular migraine
- Ménière’s disease
- Head or neck injury
- Medication effects
- Blood-pressure changes
- Neurological conditions, including stroke
Because these causes require different treatments, the description “vertigo” alone is not enough to determine whether chiropractic treatment is appropriate.
Can chiropractic care help with dizziness related to the neck?
It may help when symptoms are associated with the cervical spine, but neck-related dizziness is a diagnosis that should be made cautiously and usually after more common inner-ear and neurological causes have been considered.
The neck contains joints, muscles, and sensory receptors that provide the brain with information about head position. If neck pain, muscle guarding, arthritis, or an injury disrupts that information, some people may experience a combination of neck discomfort, lightheadedness, imbalance, or dizziness with head movement. This is sometimes called cervicogenic dizziness or cervical vertigo.
Treatment for this pattern may include gentle mobility work, posture and movement exercises, strengthening, manual therapy, and vestibular rehabilitation. The aim is usually to improve neck function and coordination rather than to “realign” the inner ear. Cleveland Clinic notes that physical therapy, vestibular rehabilitation, and, in selected cases, manual treatment may be used after other causes have been ruled out. ([my.clevelandclinic.org](https://my.clevelandclinic.org/health/diseases/23174-cervical-vertigo?utm_source=openai))
A chiropractor may be part of a coordinated care plan for a person with neck-related symptoms, particularly when care focuses on conservative movement-based treatment. However, forceful or rapid neck manipulation deserves special caution in anyone with unexplained dizziness, severe headache, vascular risk factors, recent trauma, or neurological symptoms.
Is BPPV treated by chiropractic adjustment?
Usually, BPPV is treated with a canalith repositioning maneuver rather than a traditional spinal adjustment. The Epley maneuver is one example. It uses a specific sequence of head and body positions to guide displaced inner-ear particles back to their normal location.
Clinical guidance supports repositioning procedures as initial treatment for appropriate cases of posterior-canal BPPV. Vestibular rehabilitation may also be useful, especially when balance problems continue after the spinning episodes improve. ([neuropt.org](https://www.neuropt.org/docs/default-source/vestibular-sig/vsig-physician-fact-sheets/summary-of-updated-bppv-clinical-practice-guideline.pdf?sfvrsn=d5ed5f43_2&utm_source=openai))
Some chiropractors are trained to recognize positional vertigo and perform repositioning maneuvers, while others may refer the person to a physician, physical therapist, audiologist, or vestibular specialist. The key question is not the professional title alone, but whether the provider can accurately assess the pattern of symptoms and recognize situations requiring medical evaluation.
Self-treatment videos can be misleading if the affected ear or canal has not been identified. Certain neck, back, eye, or vascular conditions may also make particular maneuvers inappropriate.
What should a proper evaluation include?
A useful evaluation begins with a detailed history. The timing and triggers of symptoms often provide important clues.
A clinician may ask:
- Does the room spin, or is the sensation more like faintness or imbalance?
- Does it begin when turning in bed or changing head position?
- How long does each episode last?
- Are there hearing changes, ringing in the ears, headache, nausea, or vision changes?
- Was there a recent fall, collision, illness, or neck injury?
- Are medications, dehydration, or blood-pressure changes possible contributors?
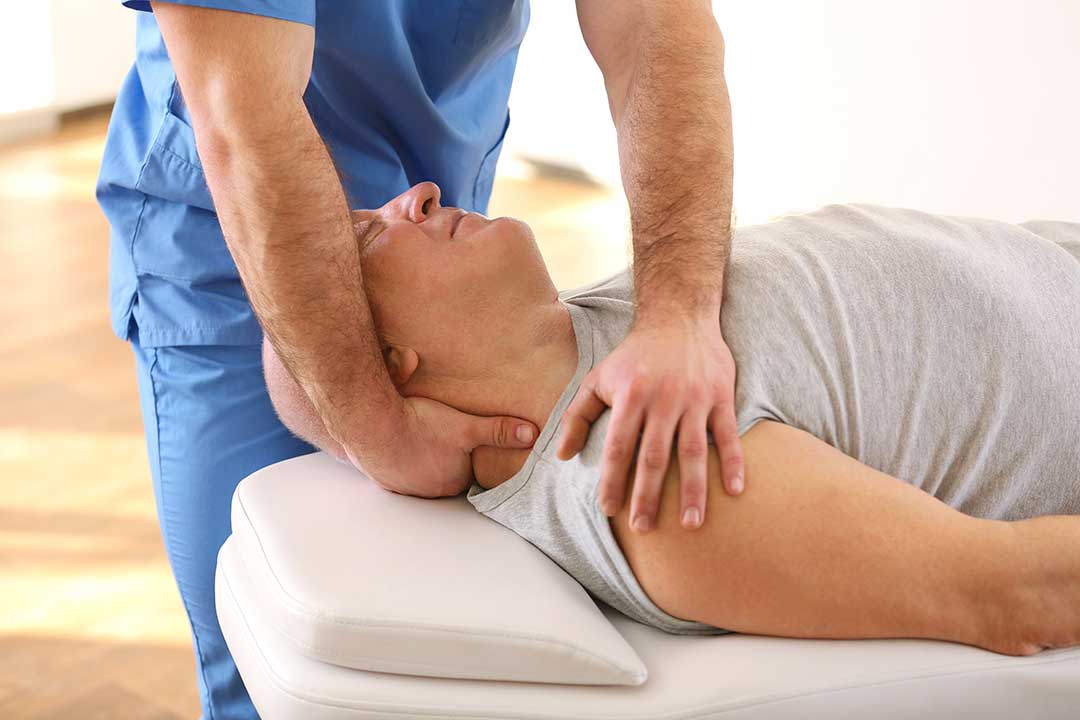
The examination may include eye-movement observation, balance testing, neck-motion assessment, neurological screening, and positional testing for BPPV. Persistent, unusual, or severe symptoms may require additional medical testing.
In the community, seasonal conditions can also affect practical safety. During icy or snowy weather, a person who is already dizzy has a higher risk of falling when walking outdoors, using steps, or moving between parked vehicles and a home. Slow transitions, adequate lighting, handrails, and avoiding ladders or slippery surfaces can reduce immediate risk while the cause is being evaluated.
When is vertigo an emergency?
New or severe vertigo should be treated as urgent when it occurs with signs that could indicate stroke or another serious condition. Seek emergency help for vertigo accompanied by:
- Facial drooping
- New weakness or numbness, especially on one side
- Trouble speaking or understanding speech
- Severe difficulty walking or loss of coordination
- Double vision or sudden vision changes
- Fainting, seizure, chest pain, or trouble breathing
- A sudden, severe headache
- Sudden hearing loss
Mayo Clinic also advises prompt medical attention when dizziness or vertigo is sudden, recurrent, prolonged, disruptive to daily life, or unexplained. ([mayoclinic.org](https://www.mayoclinic.org/symptoms/dizziness/basics/when-to-see-doctor/sym-20050886?utm_source=openai))
Neck treatment should not be used to delay emergency assessment. A stroke can sometimes resemble an inner-ear disorder, particularly when balance symptoms begin abruptly.
What can residents do during an episode?
Sit or lie down immediately to reduce the chance of falling. Move the head and body slowly, keep pathways clear, and use lights when getting up at night. Avoid driving, operating machinery, climbing, or bathing alone while symptoms are active.
Keeping a brief symptom record can help identify patterns. Note the trigger, duration, side of the body involved, associated hearing or neurological symptoms, recent illness or injury, and any medication changes.
The practical answer is that chiropractic care may have a role when dizziness is linked to neck-related dysfunction and serious causes have been excluded. It is less appropriate to assume that all vertigo comes from the spine. Inner-ear assessment, repositioning procedures, vestibular rehabilitation, medical care, or a combination of approaches may be more suitable depending on the diagnosis.
